
NFCURA
A Closed-Loop Digital Prescribing System for the Indian Healthcare Market
The Founders Behind NFCura
Technical founders with hands-on domain depth across full-stack software architecture, health data security, and direct clinical fieldwork.

Harshith R
CEO & Co-founder
Manideep Chilukuri
CTO & Co-founderTwo technical founders. 100% of the platform built in-house.
The Outpatient Reality in India Today
Decades into digital health transformation, outpatient care still ends up as uncoordinated paper files, lost prescriptions, and disconnected diagnostic reports.
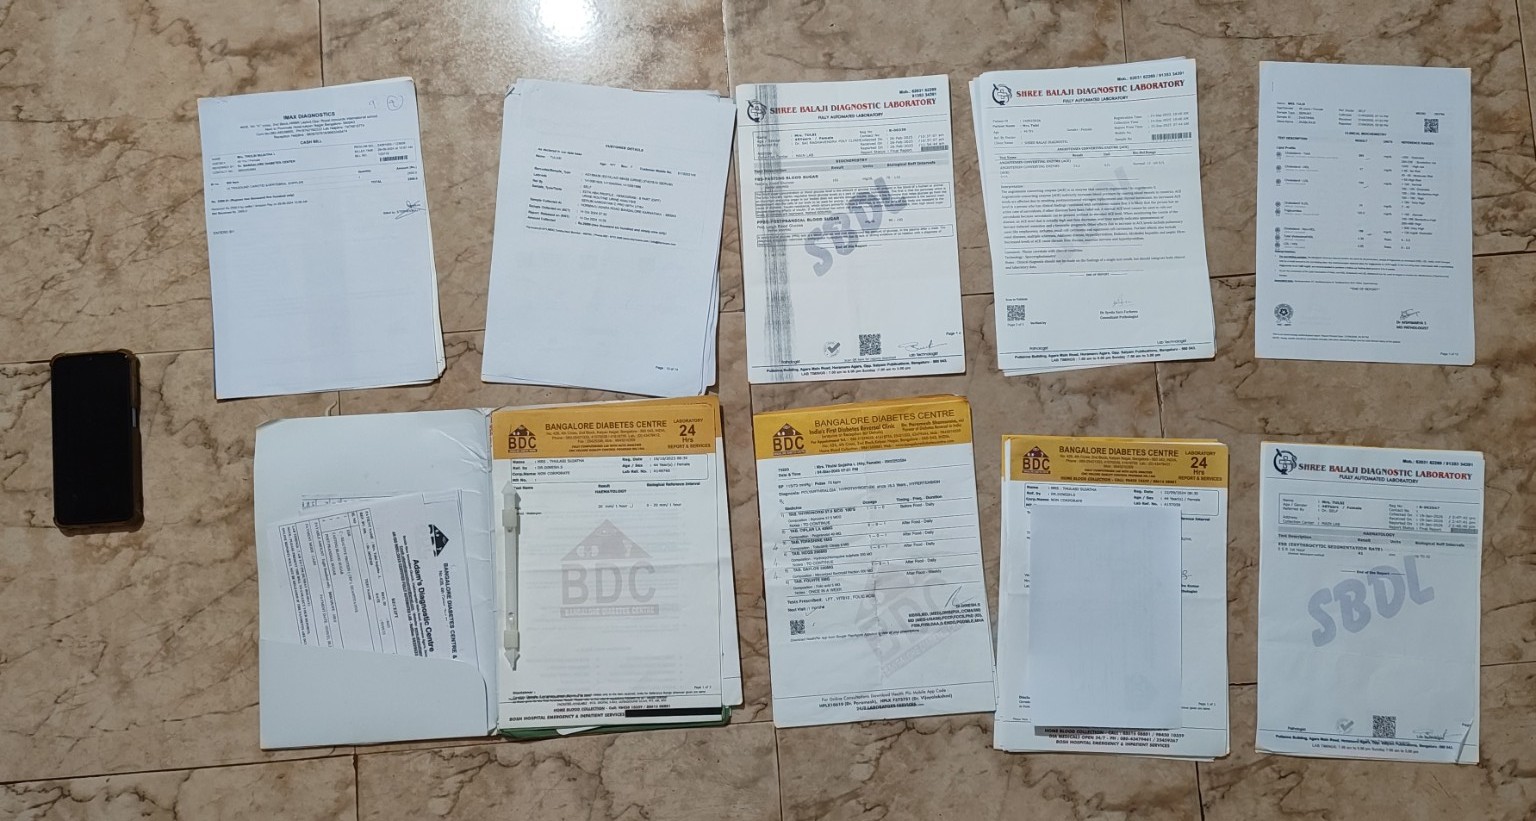
Scattered Clinical Reports
A single patient visit across clinics and diagnostic labs produces over a dozen unlinked paper slips, receipts, and test folders with zero digital coordination.

Years Trapped in Folders
Chronic patients are forced to manually store and transport kilograms of bulging paper files, fading receipts, and unindexed test histories from doctor to doctor.
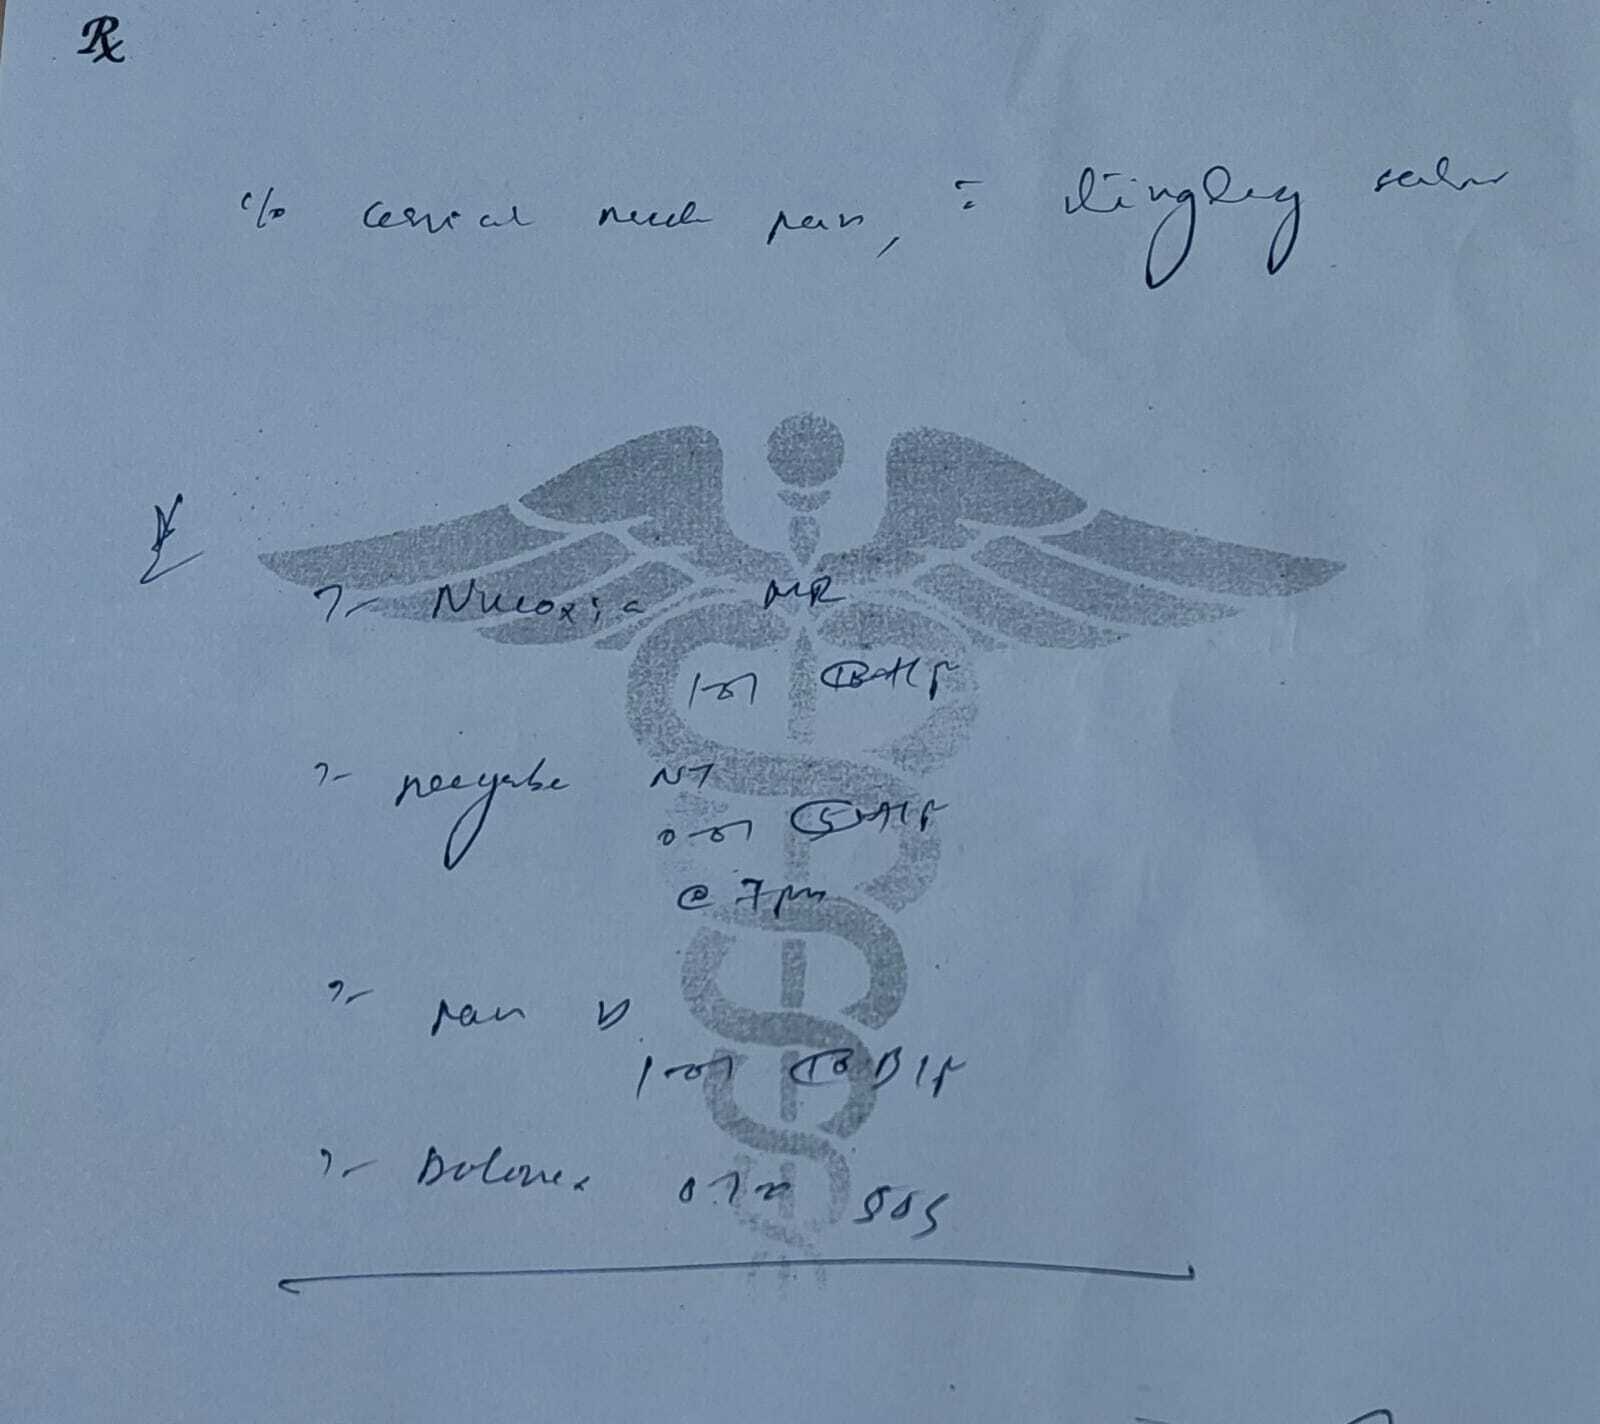
Smartphone vs. Paper Care
Patients manage payments, travel, and communication on digital smartphones — yet their life-critical healthcare journey remains trapped in physical paper slips.
The prescription exists. The connected care journey does not.
India's Outpatient Prescription Crisis
Every year, millions of handwritten prescriptions leave clinical consults with zero verification, zero tracking, and zero pharmacy coordination.
Prescription Error Rate
Alghamdi et al. (PMC): Clinical error rates drop from 35.7% in handwritten slips to just 2.5% in electronic prescribing.
Where Paper Workflows Break Down
NIH & Indian clinical survey data: 63.5% of doctors agree paper slips are error-prone; 42.6% require urgent pharmacy call-backs.
Annual Medical Errors in India
Bhutada (Indian J Crit Care Med): Millions harmed annually by uncoordinated paper slips.
Annual Global Medication Harm
WHO: Global economic burden of preventable outpatient medication and dosing errors.
Zero Doctor-Pharmacy Loop
Once a patient leaves, the clinic has zero visibility into fulfillment or drug substitutions.
The prescription exists. The digital verification and closed loop do not.
Prescription Failures in Indian Practice
Peer-reviewed studies (PubMed Central) documenting how handwriting ambiguity, lack of digital verification, and disconnected pharmacies cause real patient harm.
Doctor intended chloramphenicol for typhoid. A nurse interpreted “CP” as chloroquine phosphate for malaria. The child subsequently suffered severe liver toxicity.
A written prescription was interpreted as Ramipril 20.5 mg instead of 2.5 mg because of decimal-placement ambiguity. In the same consult, Haloperidol was dispensed instead of Nicorandil with adverse effects.
An 11-month-old infant was prescribed Dolopar 125, but the pharmacy dispensed Dolopar 250 (doubling the concentration). Discovered by the child's father only after six doses had already been administered.
Researchers recorded 1,310 medication errors across retail pharmacy chains. Prescription-stage issues included missing dose, unclear instructions, and missing prescriber details; dispensing included 58 wrong-drug errors.
17.6% of prescriptions were completely illegible. The study emphasizes that paper handwriting directly contributes to preventable medication errors and severe patient outcomes.
NFCura: Connecting the Prescription to What Happens Next
A patient-centered healthcare layer connecting doctors, patients, pharmacies and diagnostic providers through verifiable digital care events.
Doctor creates a digital prescription
Linked to the patient's Health ID and securely signed for verification.
Patient presents it at a pharmacy or lab
The provider verifies it, retrieves authorized details and fulfils the medicines or tests.
The care event is recorded
Dispensing and diagnostics link back to the patient's record, building a continuous history.
Verifiable by Design
Digital signatures help confirm prescriptions and care events haven't been altered.
Portable Health Identity
A patient-controlled Health ID with QR + NFC connects authorized healthcare interactions.
Connected Care Workflow
Doctors, pharmacies and labs share one treatment journey, not isolated workflows.
Built for Interoperability
Designed to work alongside India's digital-health ecosystem and relevant ABDM standards.
The prescription shouldn't be the end of the workflow.
It should be the beginning of a connected care journey.
A $100B+ Digital Health Wave
Rapid compounding growth across Indian healthcare IT, pharmacy management systems, and clinical infrastructure.
Projected 10-Year Market Size
Grand View Research & IMARC: India Digital Health compounding to $107B+ by 2033; Healthcare IT to $112B+ by 2034.
Annual Growth Rate by Sector (CAGR %)
High compounding momentum across clinical IT (19.7%), digital health (25.1%), and pharmacy management.
Total Addressable Market
India Pharmacy Management Systems market projected by 2035 (Market Research Future).
Serviceable Addressable
Outpatient e-prescribing and pharmacy verification segment (~20% of TAM) across urban clinical hubs.
5-Year Target
5% penetration of SAM with blended SaaS subscription + per-prescription transaction ARPU.
Positioned at the intersection of a $100B+ digital health wave and mandatory clinical digitization.
90 Crore ABHA Accounts & Chronic Burden
India's digital health stack has hit critical mass, while an explosion in chronic conditions requires closed-loop medication management.
ABHA Digital Health Identity Trajectory
PIB India: ABHA accounts scaled from 14.7Cr (2021) to 90Cr+ (900 Million) across 256K+ verified healthcare facilities.
Chronic Outpatient Disease Prevalence (%)
Springer: 46.1% comorbid cases face high polypharmacy risks, requiring strict lifelong adherence tracking.
ABHA Identity Base
PIB India: Over 65% of citizens registered with universal digital health identifiers.
eSanjeevani Teleconsults
IMARC: Massive national transition to electronic, remote healthcare consultations.
HTN + Diabetes Overlap
Springer: Strict clinical need for closed-loop prescription and refill adherence.
National identity scale + lifelong medication needs = the inevitable shift to verified prescribing.
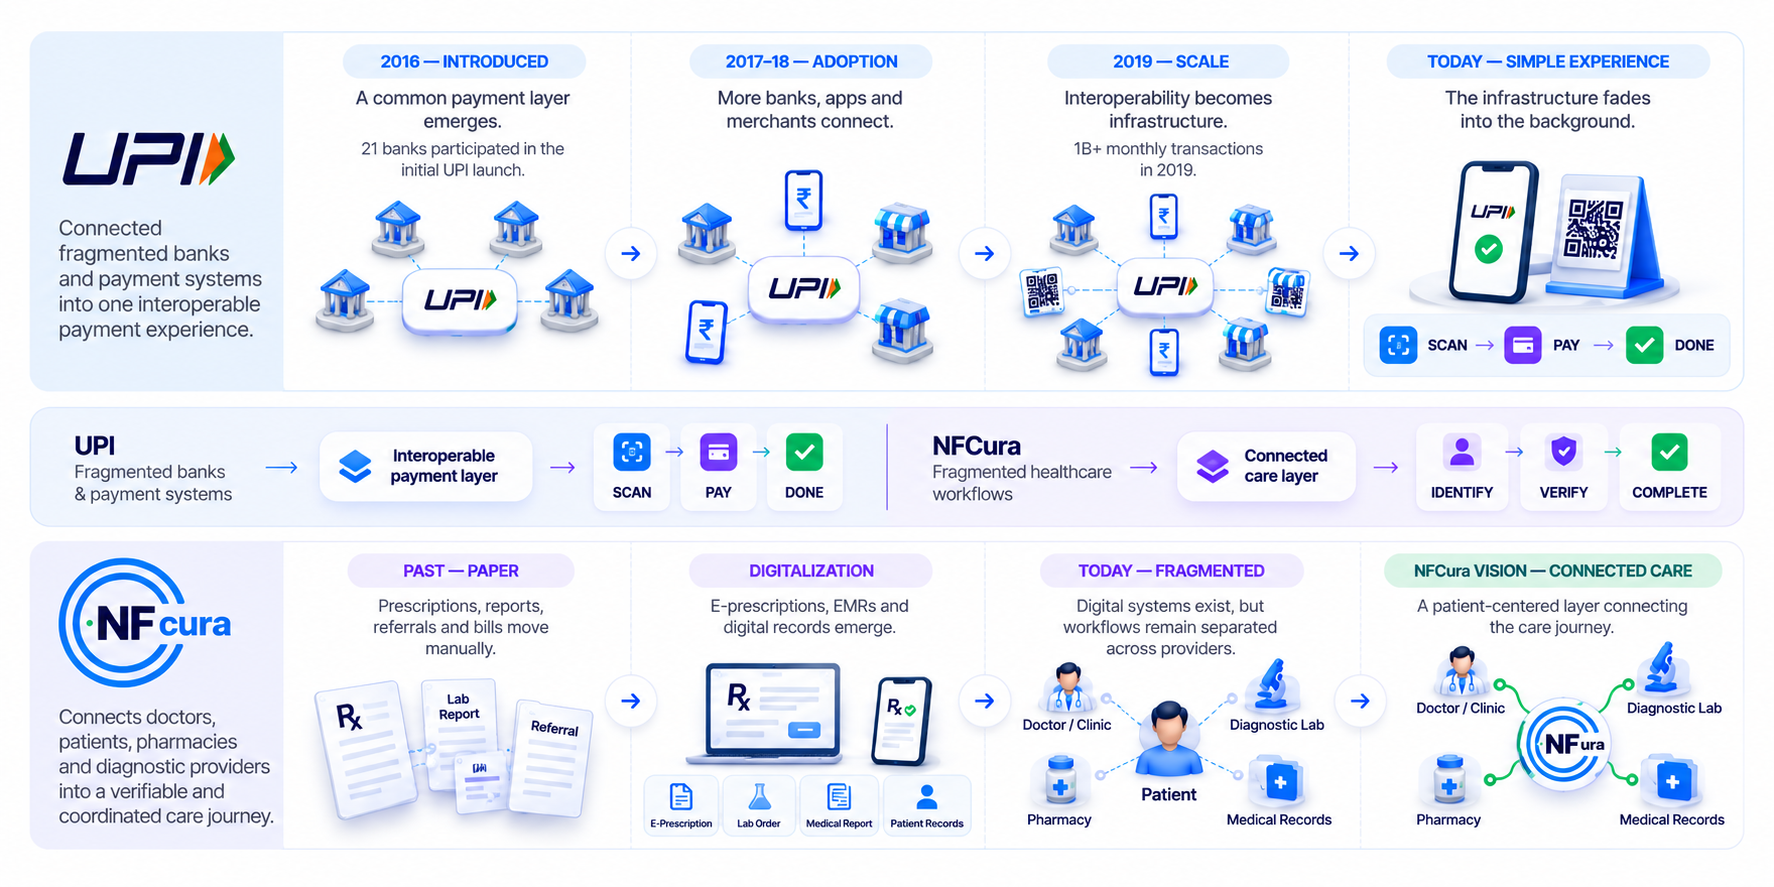
Built to Scale: Lightweight Healthcare Data Infrastructure
One prescription is only ~50 KB of structured data — keeping the core healthcare record lightweight while medical files live separately in secure object storage.
Conservative planning assumption for a fully structured, queryable clinical payload.
Structured clinical records stay lightweight in the database. Diagnostic PDFs, scans, and heavy medical files live in separate secure object storage.
Predictable Infrastructure Scaling
* Illustrative Firestore Standard pricing assumptions ($0.18/GiB-mo storage, $0.30/1M reads, $0.90/1M writes). Excludes index overhead, network egress, compute, and other Firebase services. Actual billing varies by region and usage.
/rx/<token>) — not embedded medical files.NFCura separates the healthcare record from the healthcare file — keeping core data lightweight while supporting rich medical care.
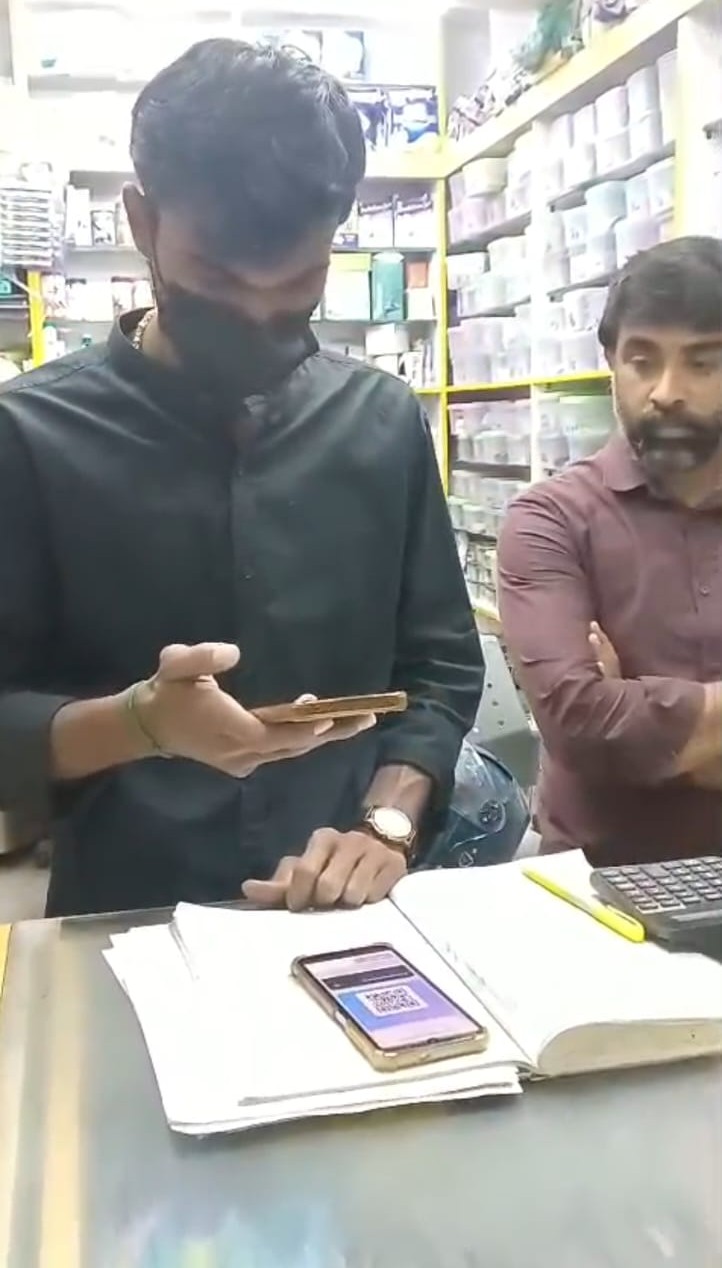
Advisory Consultations & Retail Pharmacy Feedback
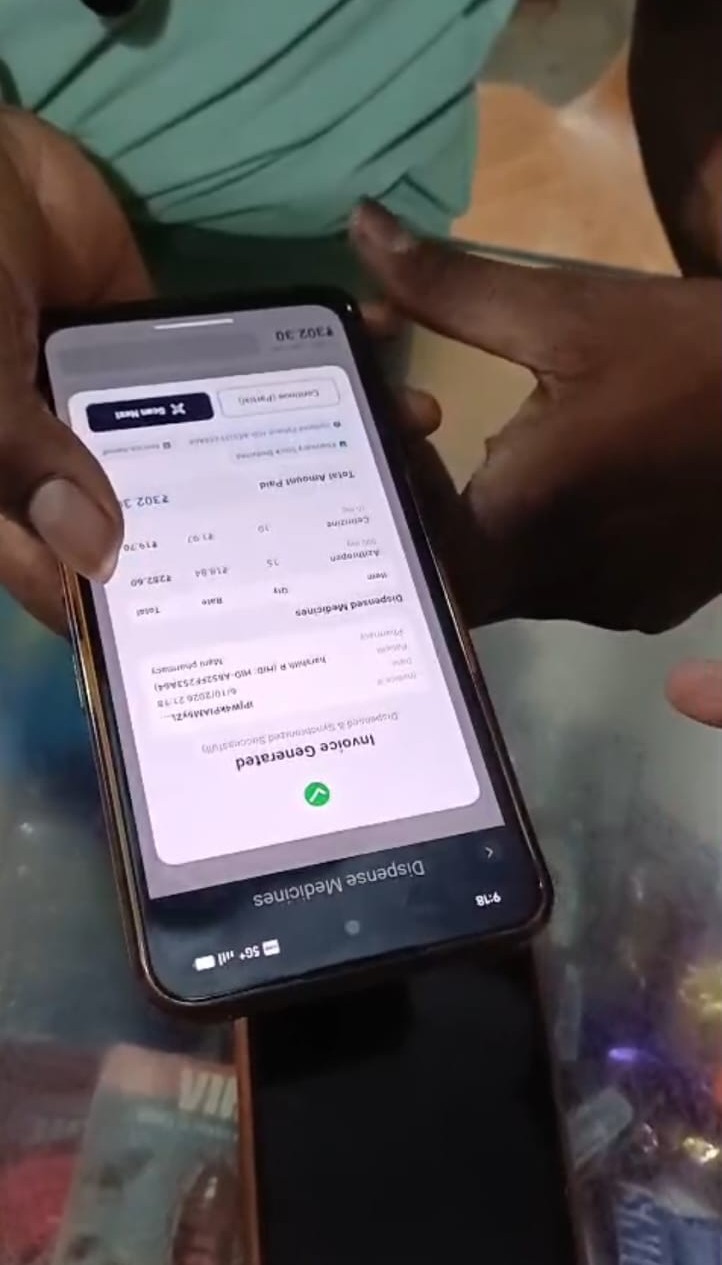
Direct photographic proof from university faculty discussions and retail pharmacy feedback sessions.
Department Heads & Senior Professors




Retail Pharmacy Feedback


The Universal Health Passport: Patient-Owned & Verified
A frictionless mobile passport that replaces fragmented paper files with structured digital prescriptions, instant pharmacy verification, and continuous history.

Digital Health ID
Patient-owned universal health passport with QR and linked ABHA credentials.

Women's Care Enabled
Dedicated Women's Care mode with discrete privacy settings and tailored wellness tracking.
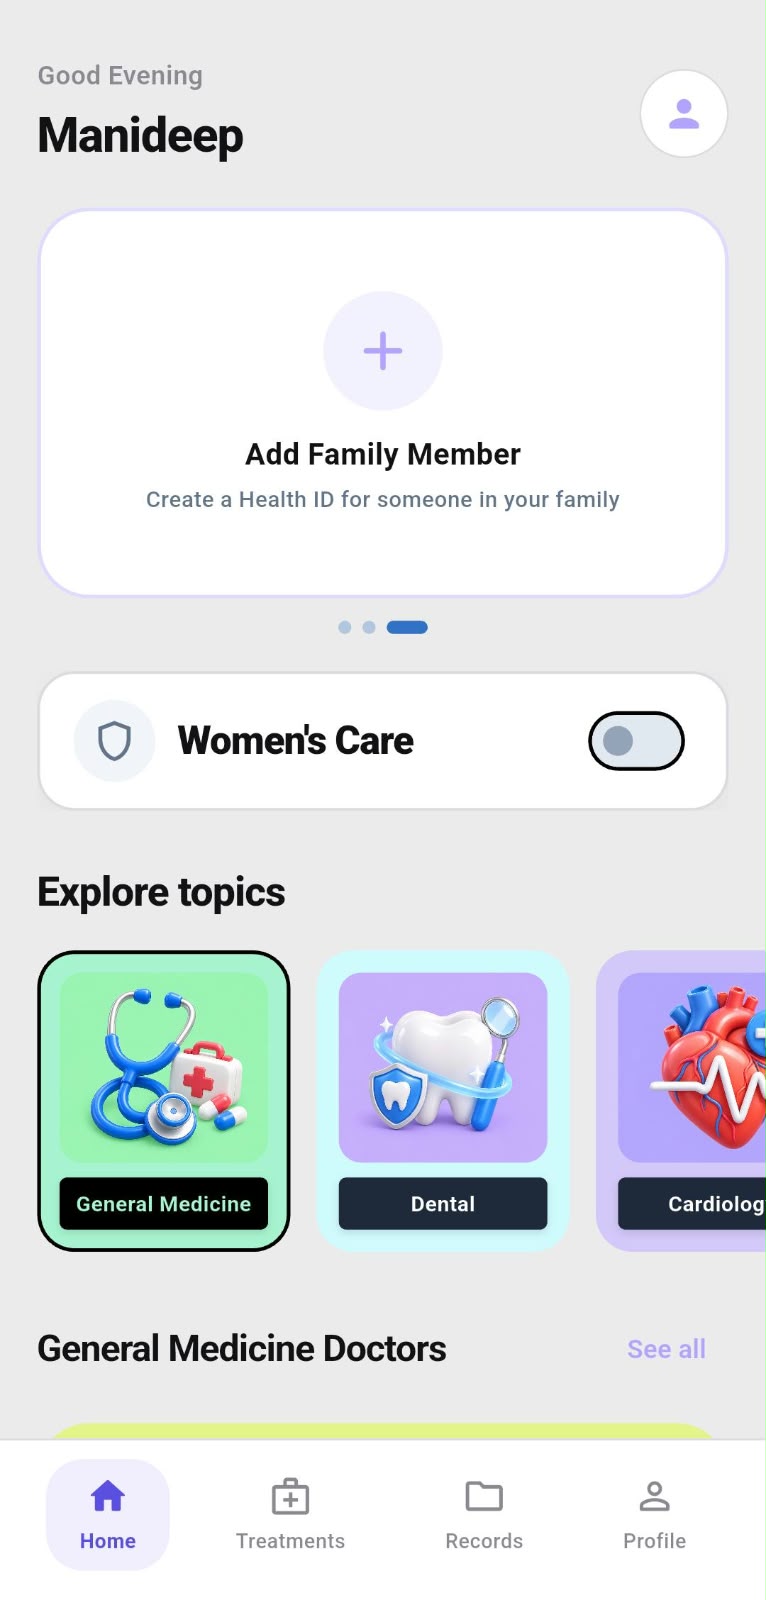
Add Family Member
Multi-profile card to create and manage Health IDs for family members and dependents.
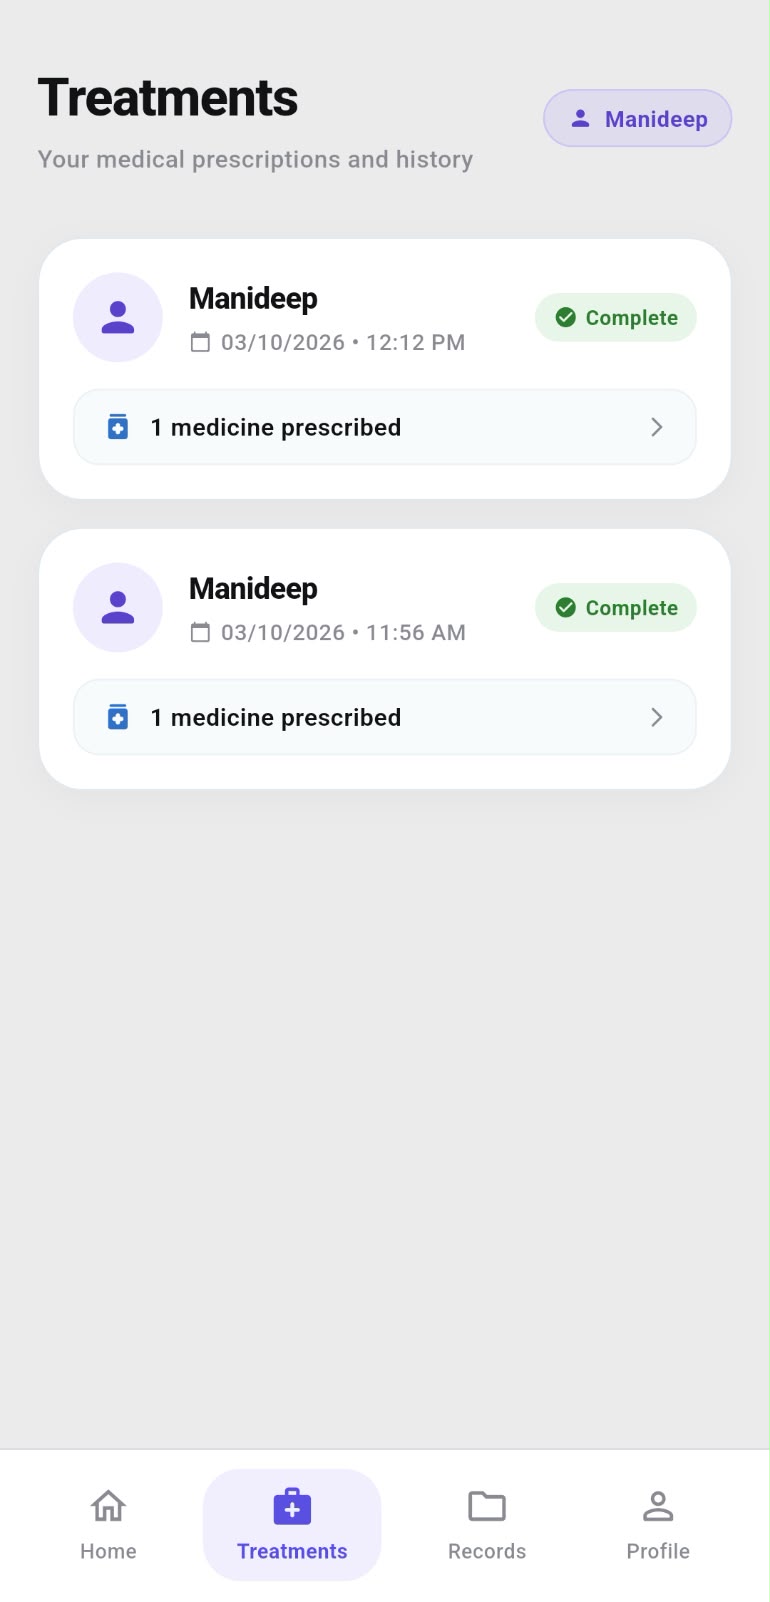
Treatments & History
All active and past medical prescriptions organized under patient and family profiles.
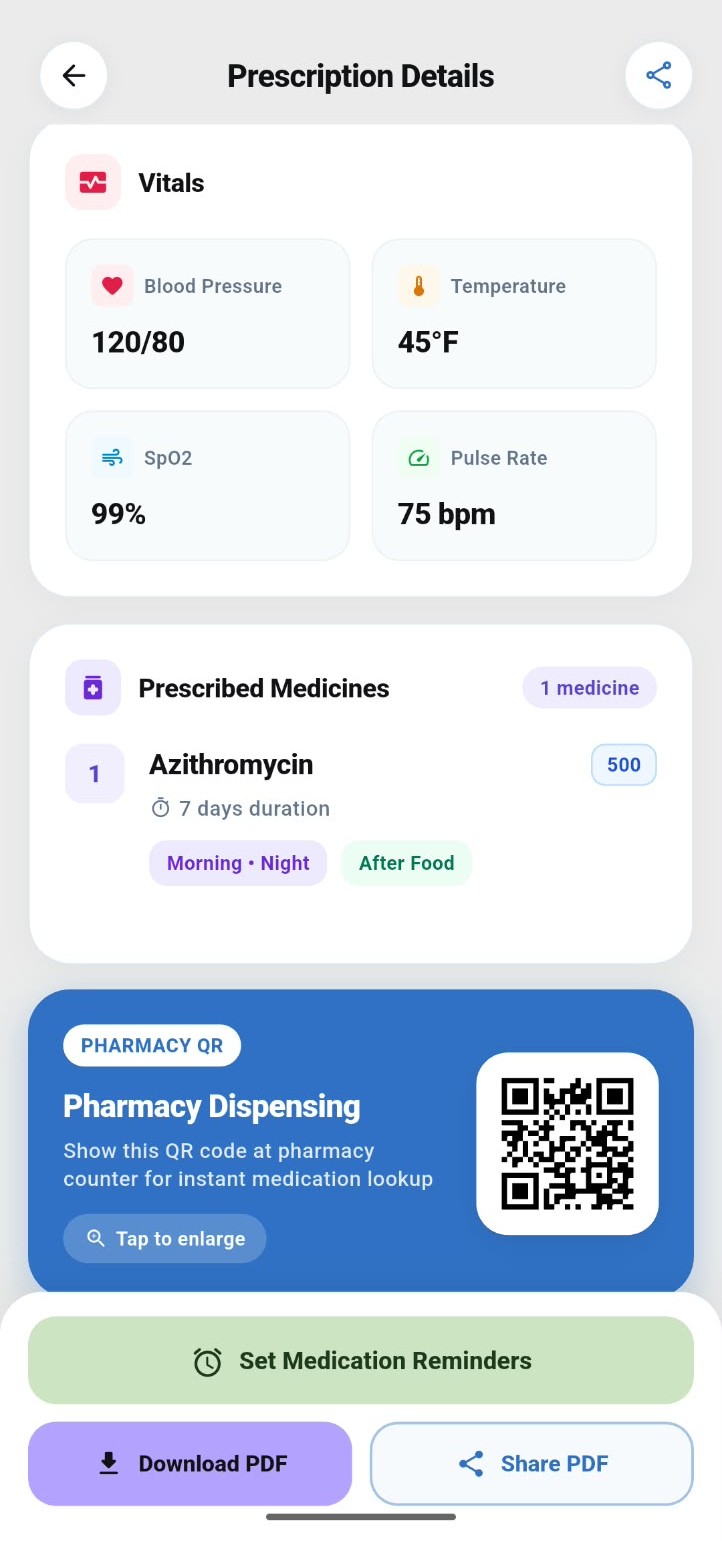
Prescription Details
Inside the prescription: structured medicines, dosages, duration, and linked clinical vitals.
The Connected Pharmacy: Zero-Friction Counter Dispensing
A high-speed counter suite for retail chemists: instant QR verification, real-time inventory deduction, live invoice calculation, and anti-fraud duplicate prevention.
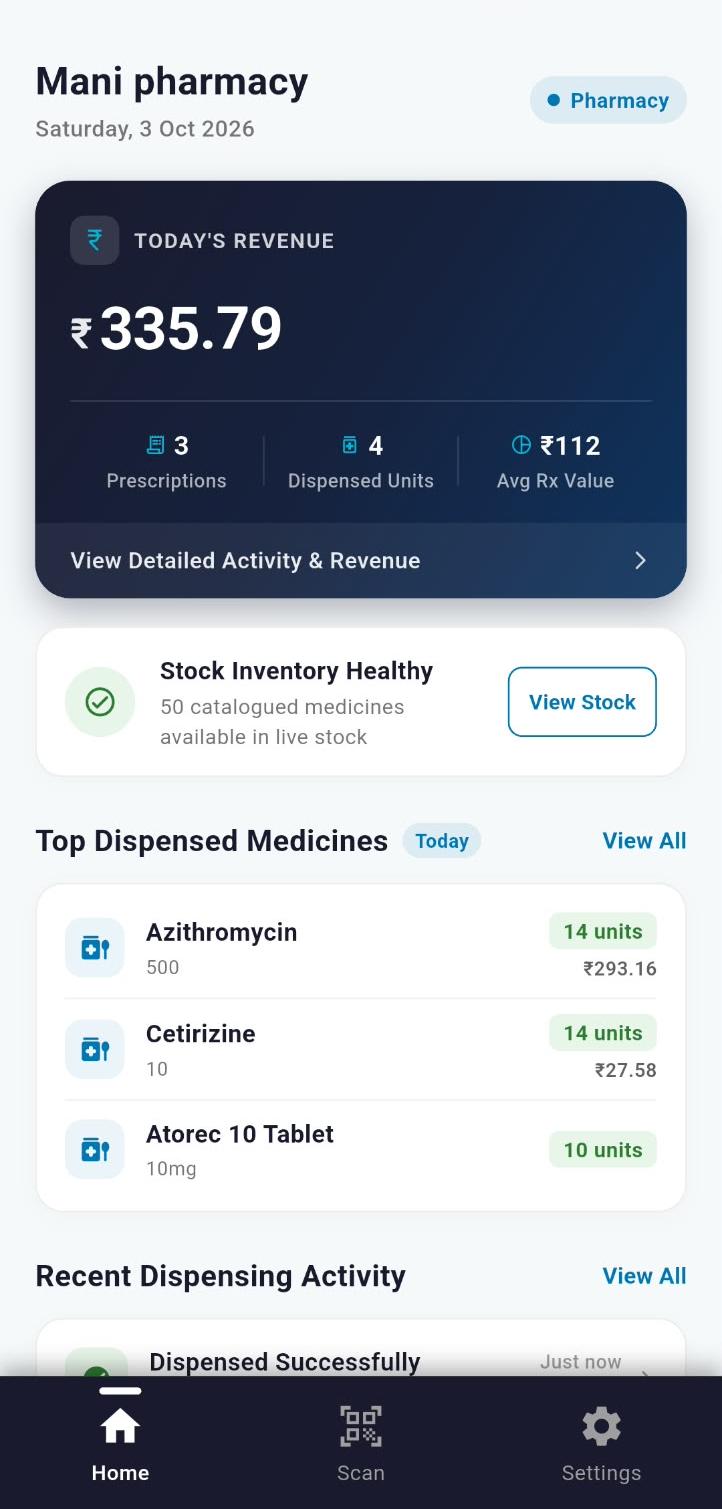
Counter Dashboard
Daily revenue, dispensed prescription volume, live catalogued stock status, and rapid workflow shortcuts.
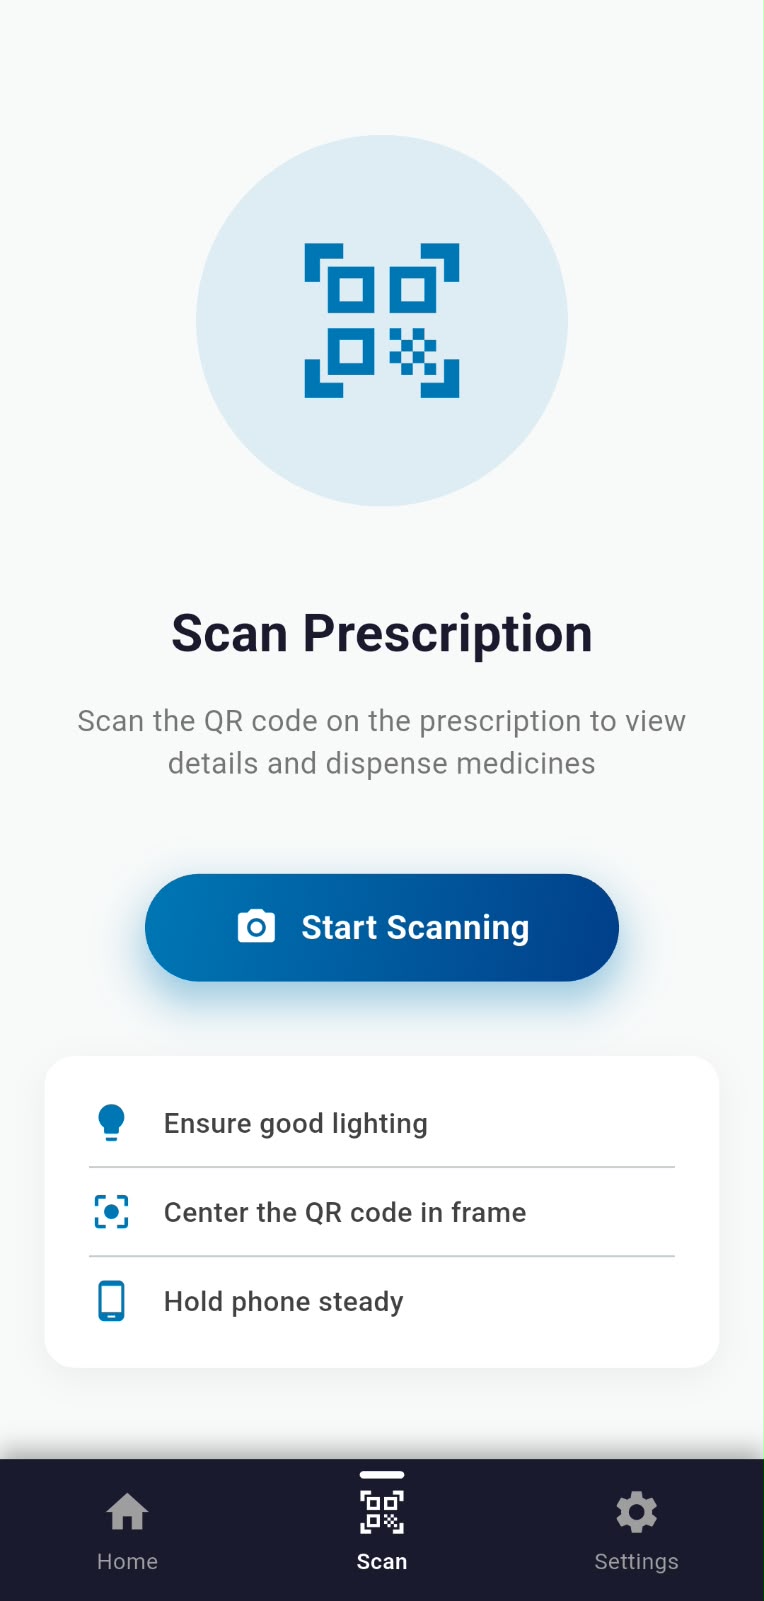
Scan Prescription
Instant camera scanner to scan patient QR codes or prescription tokens and pull verified doctor orders.
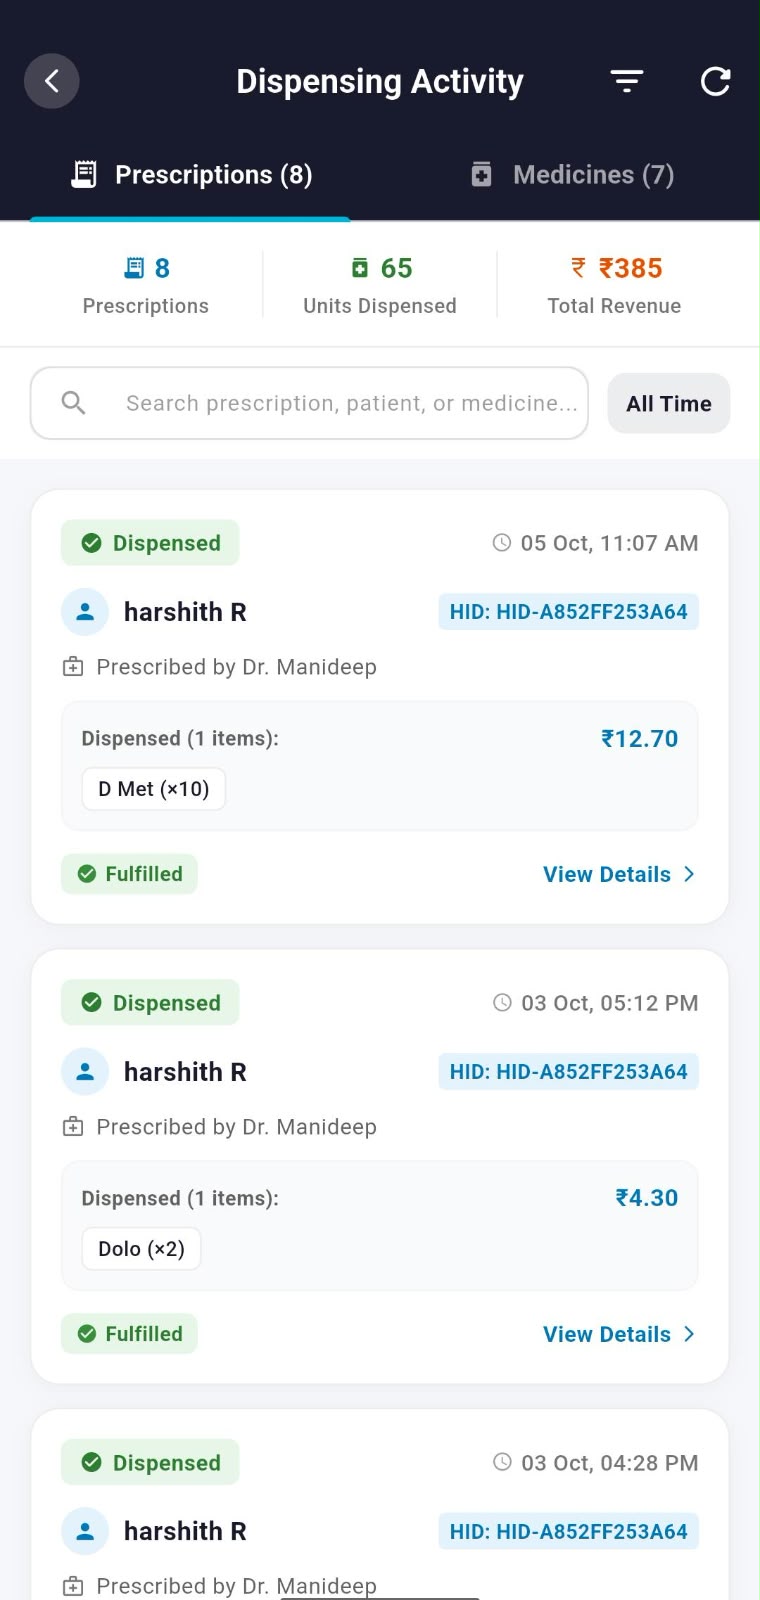
Dispensing Activity
Comprehensive audit logs tracking patient HIDs, prescribing doctors, dispensed items, and fulfillment timestamps.
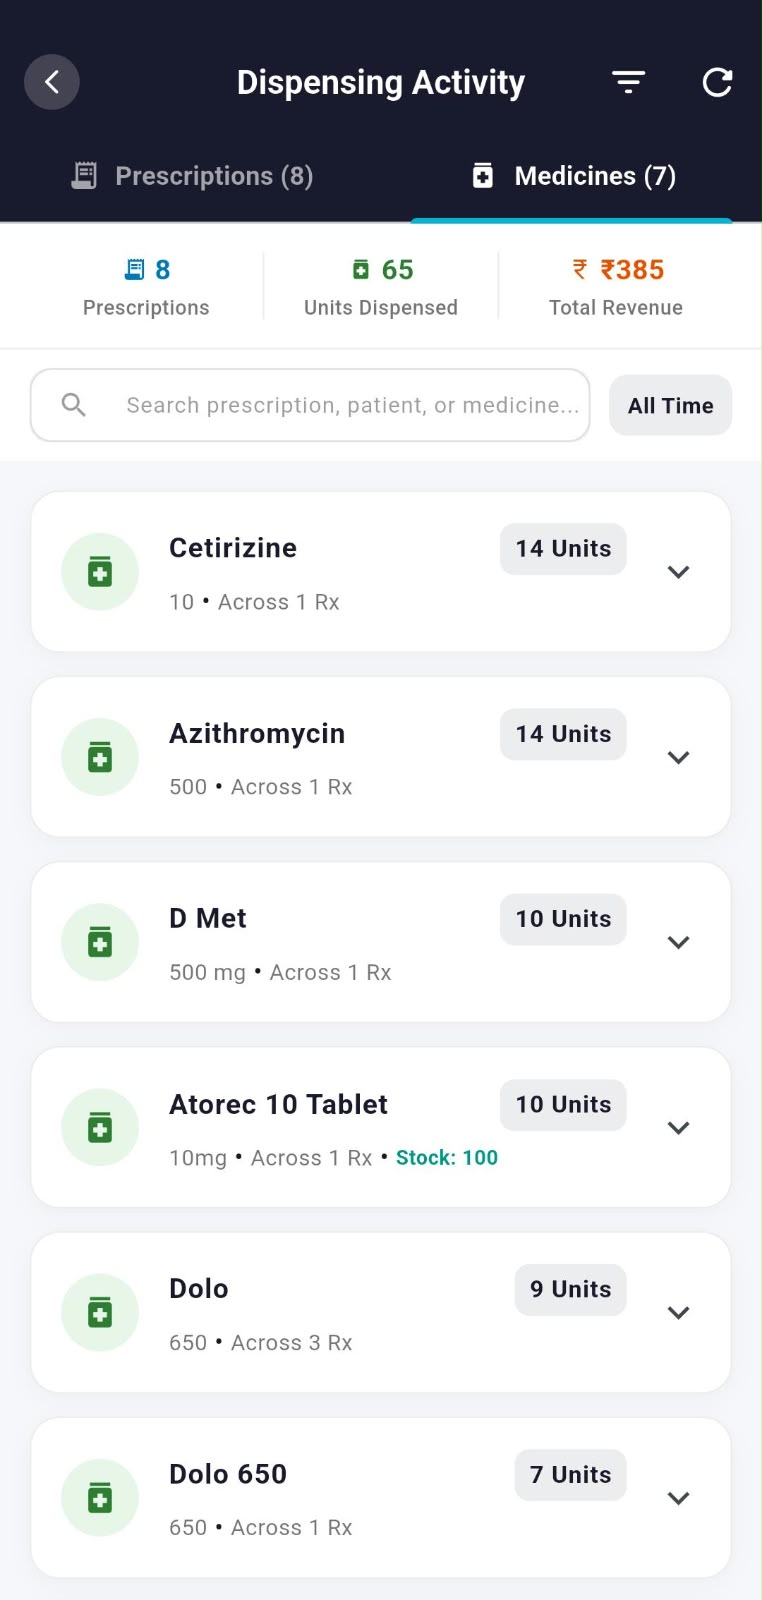
Medicine Stock Audit
Live drug-level inventory breakdown tracking unit dispensing volumes across all active prescriptions.
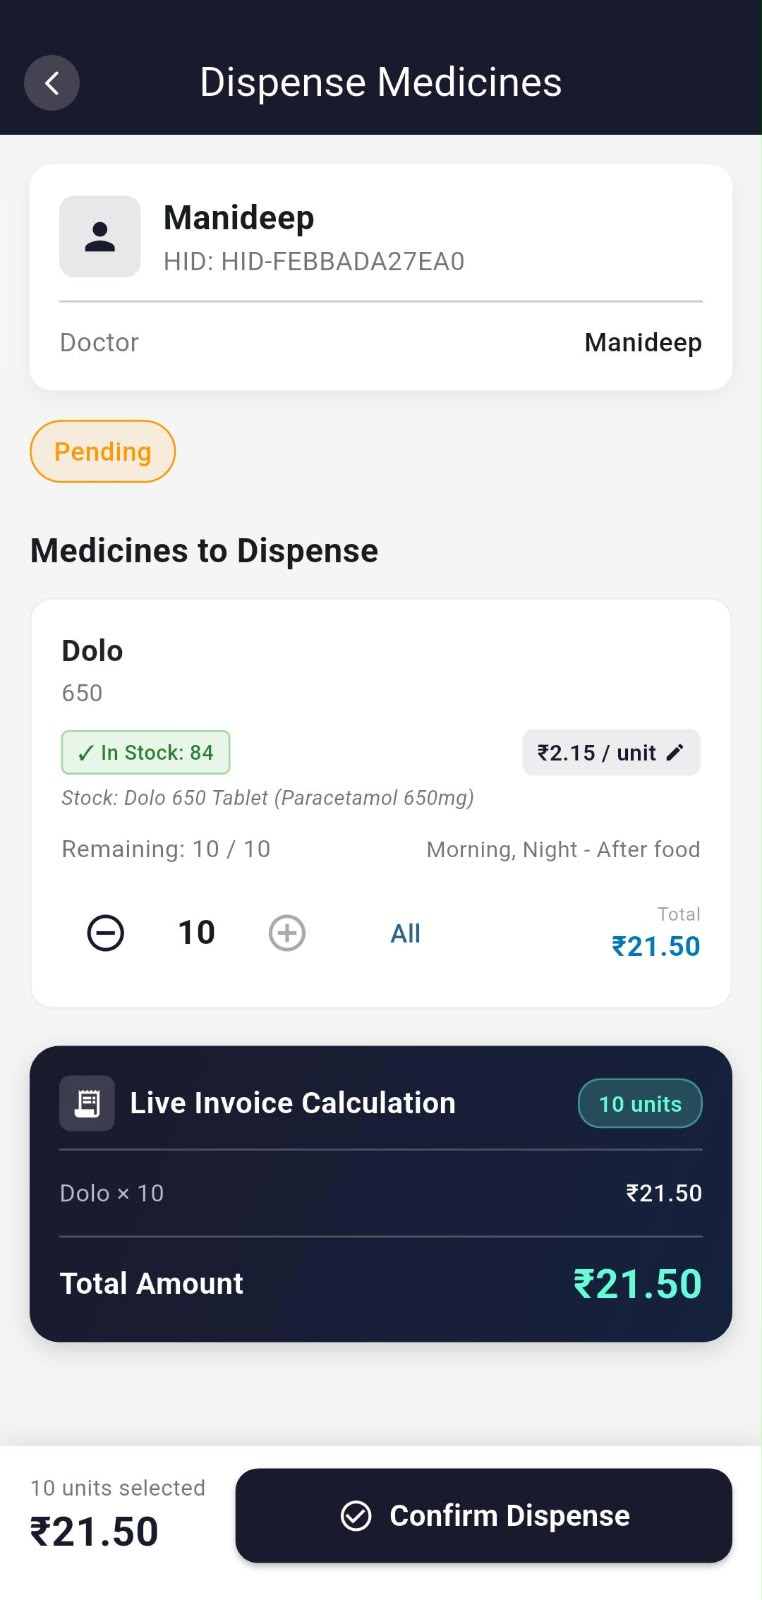
Dispense & Billing
Interactive unit quantity adjustments, live stock checks, real-time invoice calculations, and one-tap fulfillment.
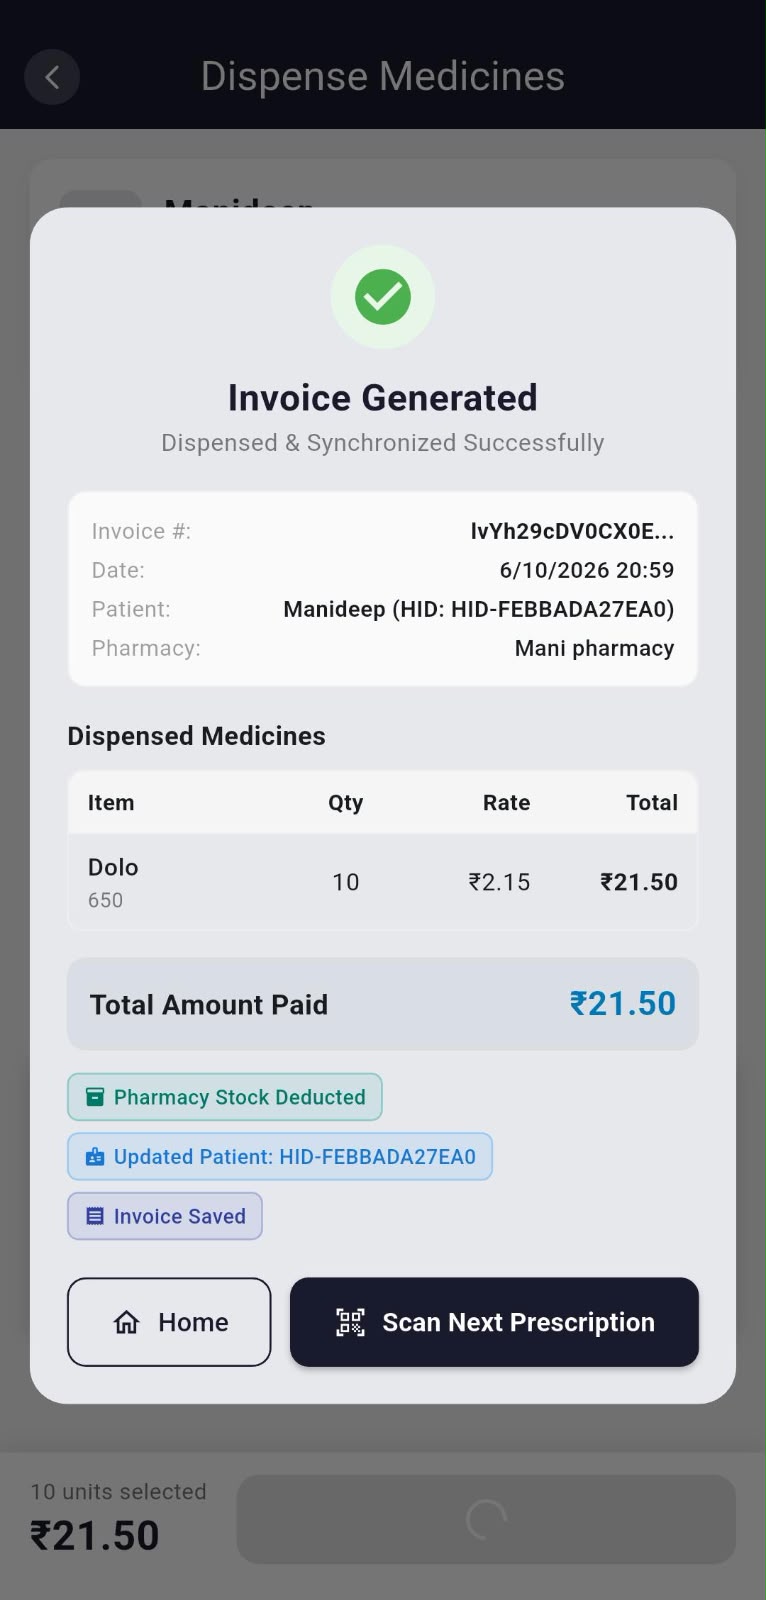
Invoice Generation
Auto-generated digital invoice with immediate pharmacy inventory deduction and patient record synchronization.
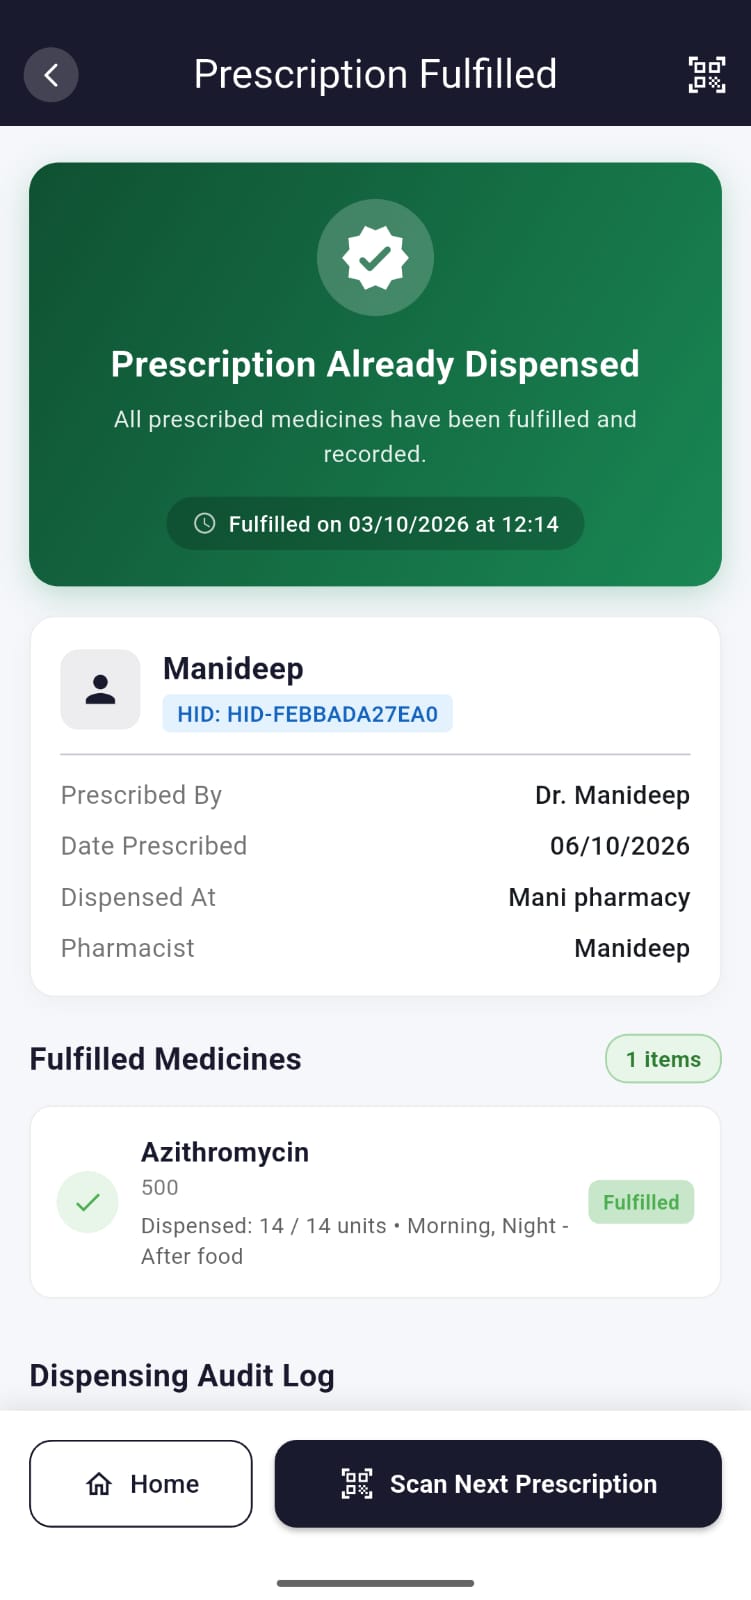
Anti-Duplication Guard
Tamper-proof safeguard alerting pharmacist if a prescription was already fulfilled, preventing drug misuse.
The Doctor Workspace: Sub-Second Lookup & Structured Prescribing
A high-speed clinical interface designed for outpatient doctors: scan patient health cards, review automated AI summaries and past history, and generate structured prescriptions in seconds.
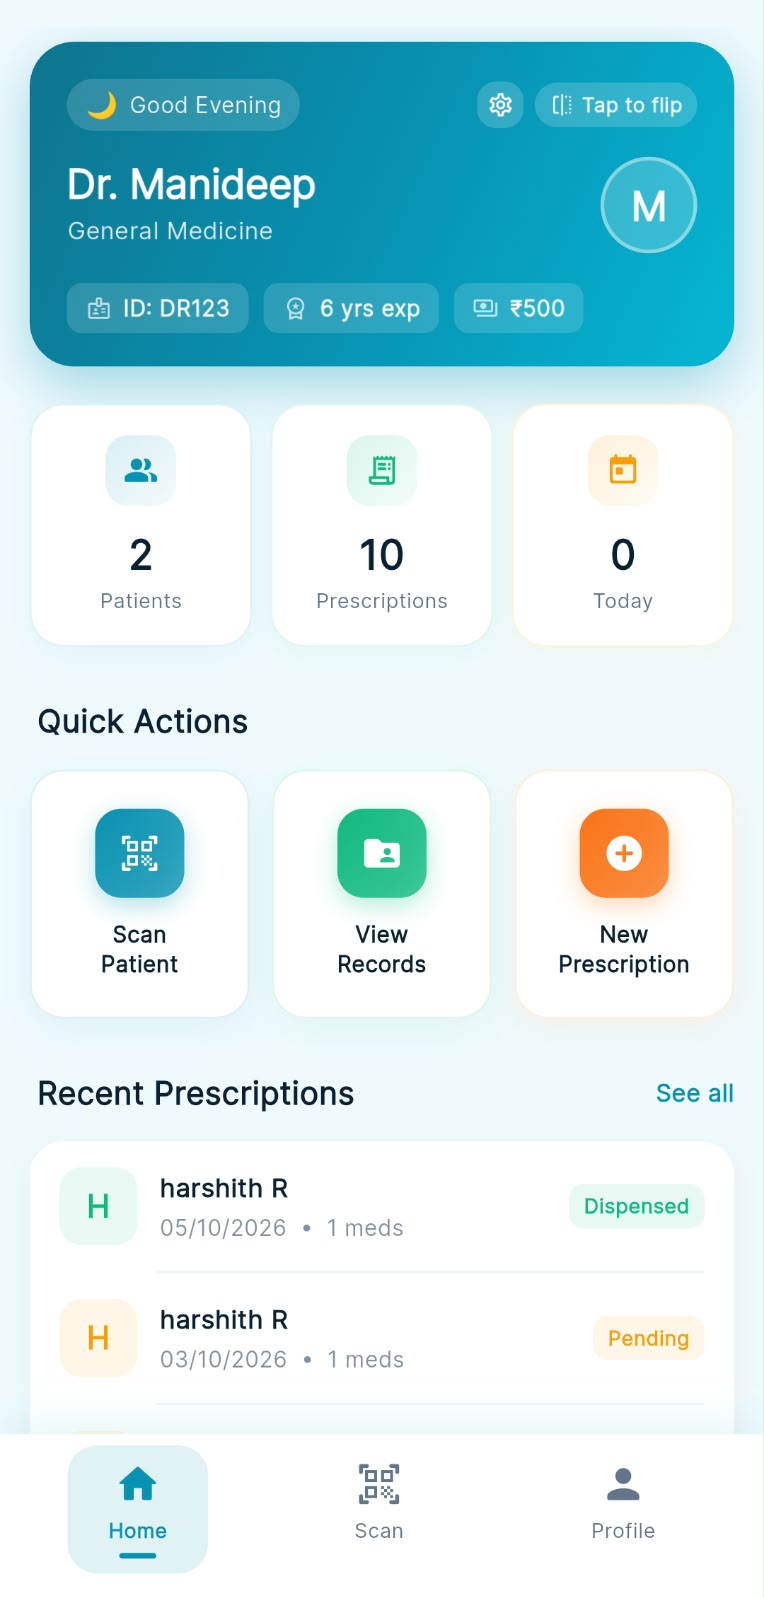
Doctor Dashboard
Clinical practice overview with live patient queues, daily prescription counts, and fast workflow shortcuts.
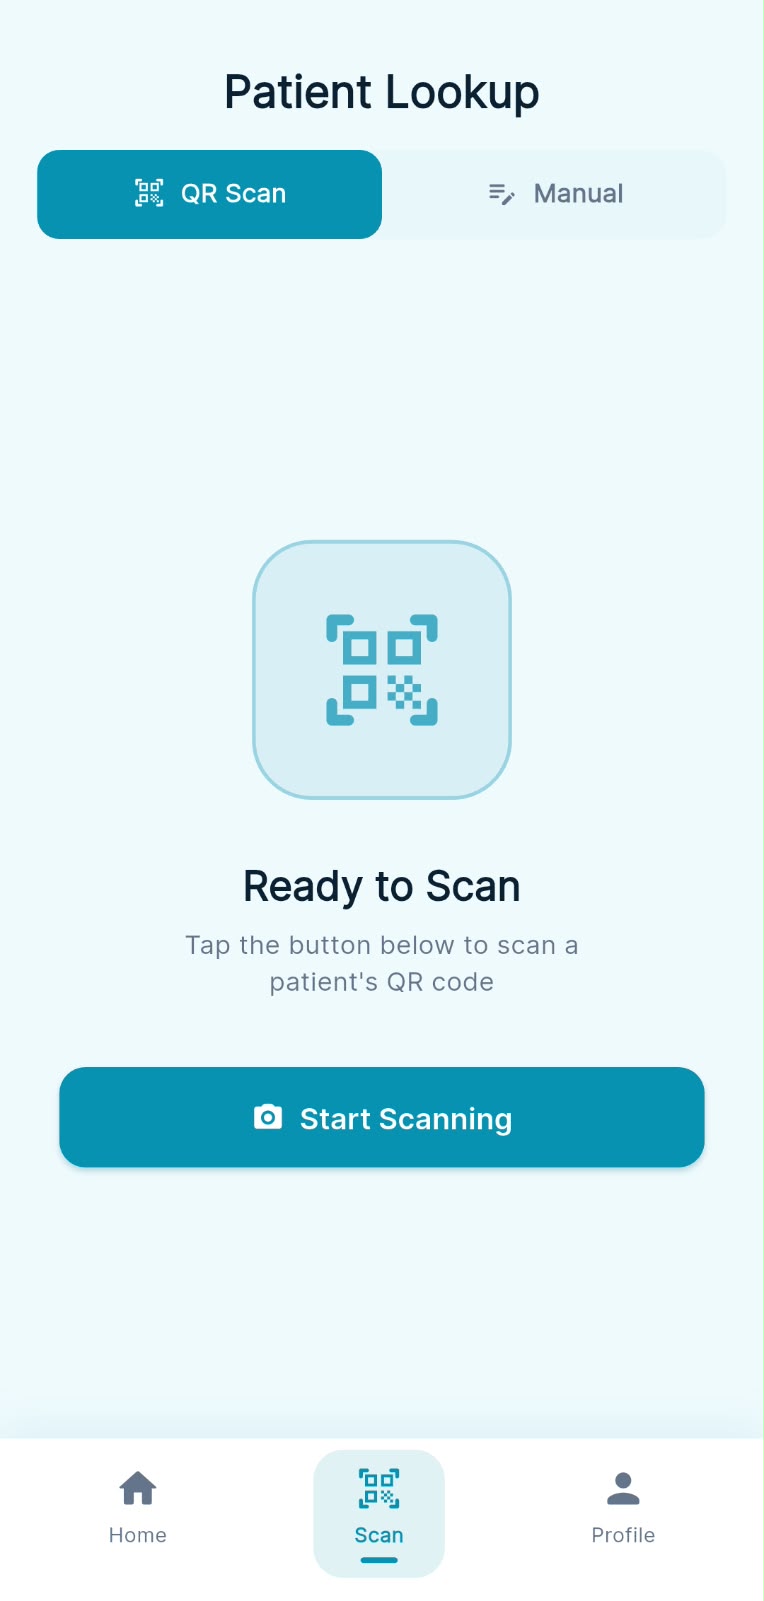
Patient Lookup
Frictionless patient identification via QR health card scanning or ABHA/HID direct search.

Instant QR Scanner
Sub-second camera scanner reading encrypted physical health cards to instantly retrieve verified history.
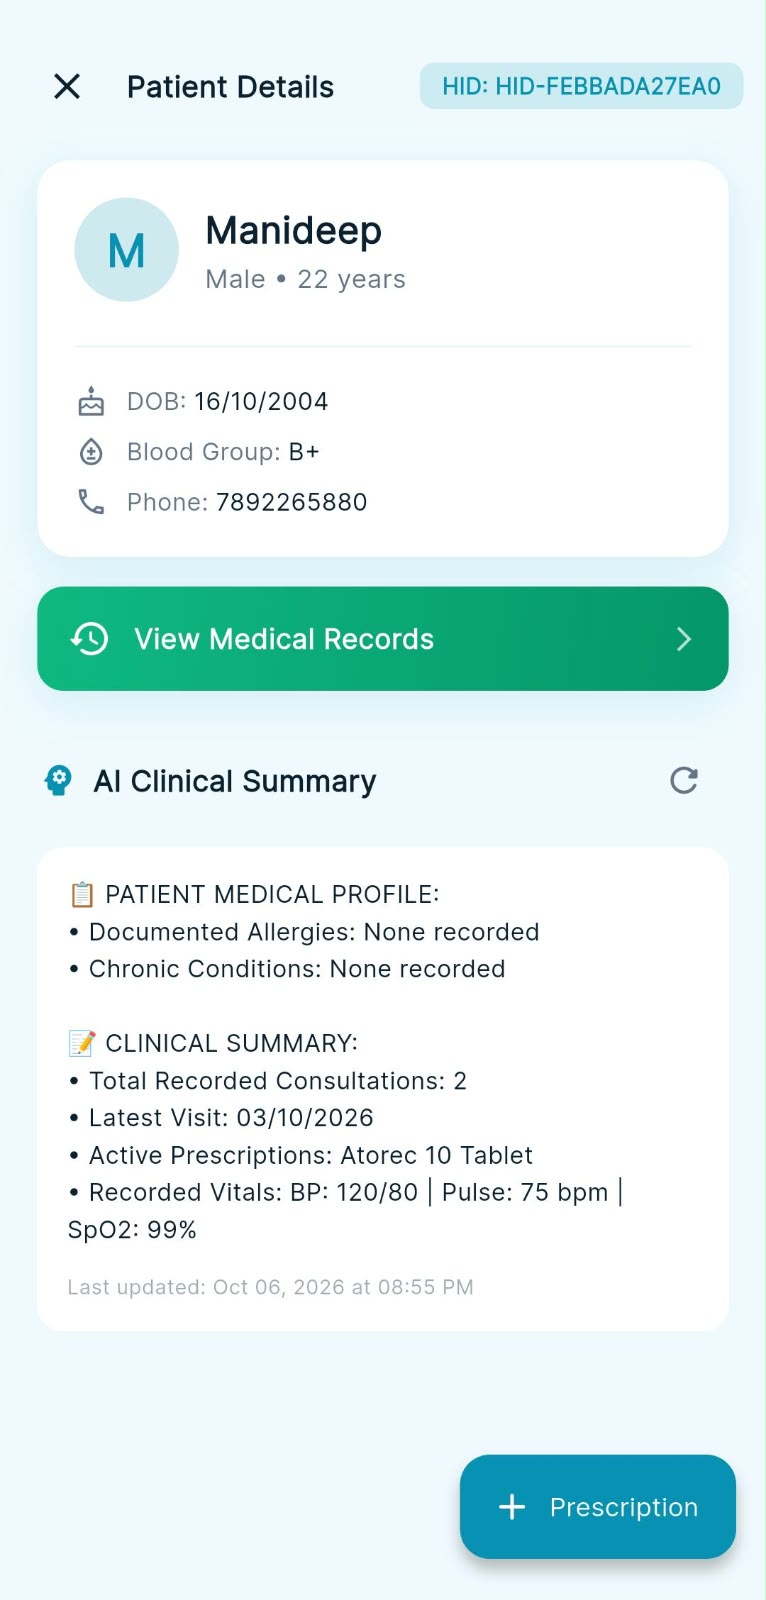
AI Clinical Summary
Instant patient chart detailing allergies, chronic conditions, recorded vitals, and longitudinal AI synthesis.
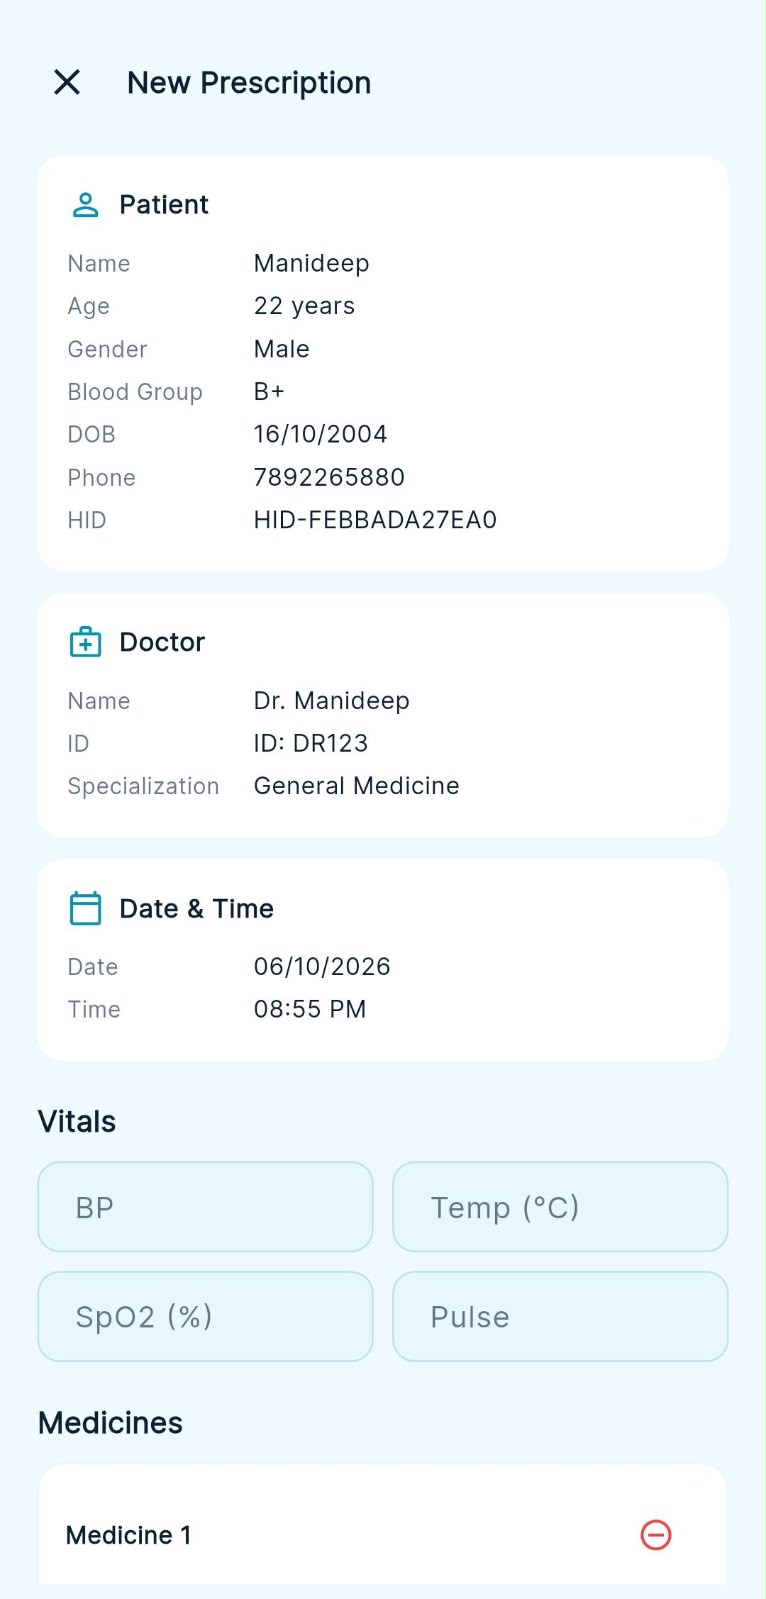
Digital Rx & Vitals
Streamlined entry for multi-parameter vitals (BP, Temp, SpO2, Pulse) and structured medication regimens.
Monetizing the Connected Care Journey
Recurring clinic SaaS forms the base. Usage and provider-network activity expand revenue.
Subscription Pricing Structure
Recurring subscription = predictable base revenue
Patients stay free to maximize adoption and network density.
*Illustrative pricing · *Revenue model to be validated through pilotsRecurring SaaS builds the base. Usage expands revenue. The provider network creates the upside.
Beyond the Digital Prescription
From Working MVP to Connected Care Network
Start with focused clinic pilots, validate the workflow, then build the infrastructure and team required to scale.
From Paid Pilots to a Scalable Care Network
Clinic SaaS creates recurring revenue. Usage and provider-network activity expand revenue as adoption grows.
Recurring subscription for clinic workflow and connected care tools.
Prescription creation, verification and dispensing workflows.
Pharmacy verification and diagnostic booking coordination.*
Raising ₹1.5 Crore Pre-Seed
18 months of operational runway to transition our working MVP into production, run clinical pilots, and establish a repeatable connected-care network.
Build the production platform
- Backend infrastructure & core microservices
- Secure NFC tap protocols & credential verification
- EHR interoperability & hospital OPD integrations
Turn MVP into repeatable adoption
- 50 clinic onboarding & doctor workflow setups
- 150 retail pharmacy & counter reader rollouts
- Provider success support & on-ground field ops
Prepare for healthcare-scale deployment
- ABDM Milestone 1–3 regulatory certification
- CERT-In security audits & penetration hardening
- DPDPA compliance & healthcare data governance
Keep platform running efficiently
- High-availability cloud hosting & server telemetry
- Smart card buffer & NFC validation hardware
- Administration, tooling & reserve contingency
Data Sources & Verified Citations
Every metric, prevalence rate, and financial projection in this deck is grounded in official government records, peer-reviewed medical literature, or primary market research.
| Authority Type | Specific Published Sources & Verified Citations |
|---|---|
| Government & Official | Press Information Bureau (PIB India — ABDM May 2026 release), Ministry of Health and Family Welfare (MoHFW), National Health Authority (NHA). |
| Market Research Firms | Grand View Research (Digital Health 2024–33), IMARC Group (Healthcare IT 2025–34), MarketsandMarkets, Market Research Future (MRFR), Research and Markets. |
| Peer-Reviewed Literature | Springer Systematic Review & Meta-Analysis (2026), PMC / NIH (Alghamdi et al. 2015), Indian Journal of Critical Care Medicine (Bhutada 2020), JAMIA Open. |
| Industry Reports & Media | World Health Organization (Medication Without Harm 2024), CB Insights (State of Digital Health 2025), LinkedIn / Venture Intelligence, Economic Times, Business Wire. |
Zero fabricated statistics. Zero invented citations. All figures and projections are directly traceable to published institutional documentation.
NFCURA